OHIP billing·
Error Code VJ7: What Stale Dating Means for Your OHIP Claims and How to Recover Revenue
A VJ7 error code means your OHIP claim aged past the 3-month submission window. Here is exactly how to recover that revenue before it becomes unrecoverable.
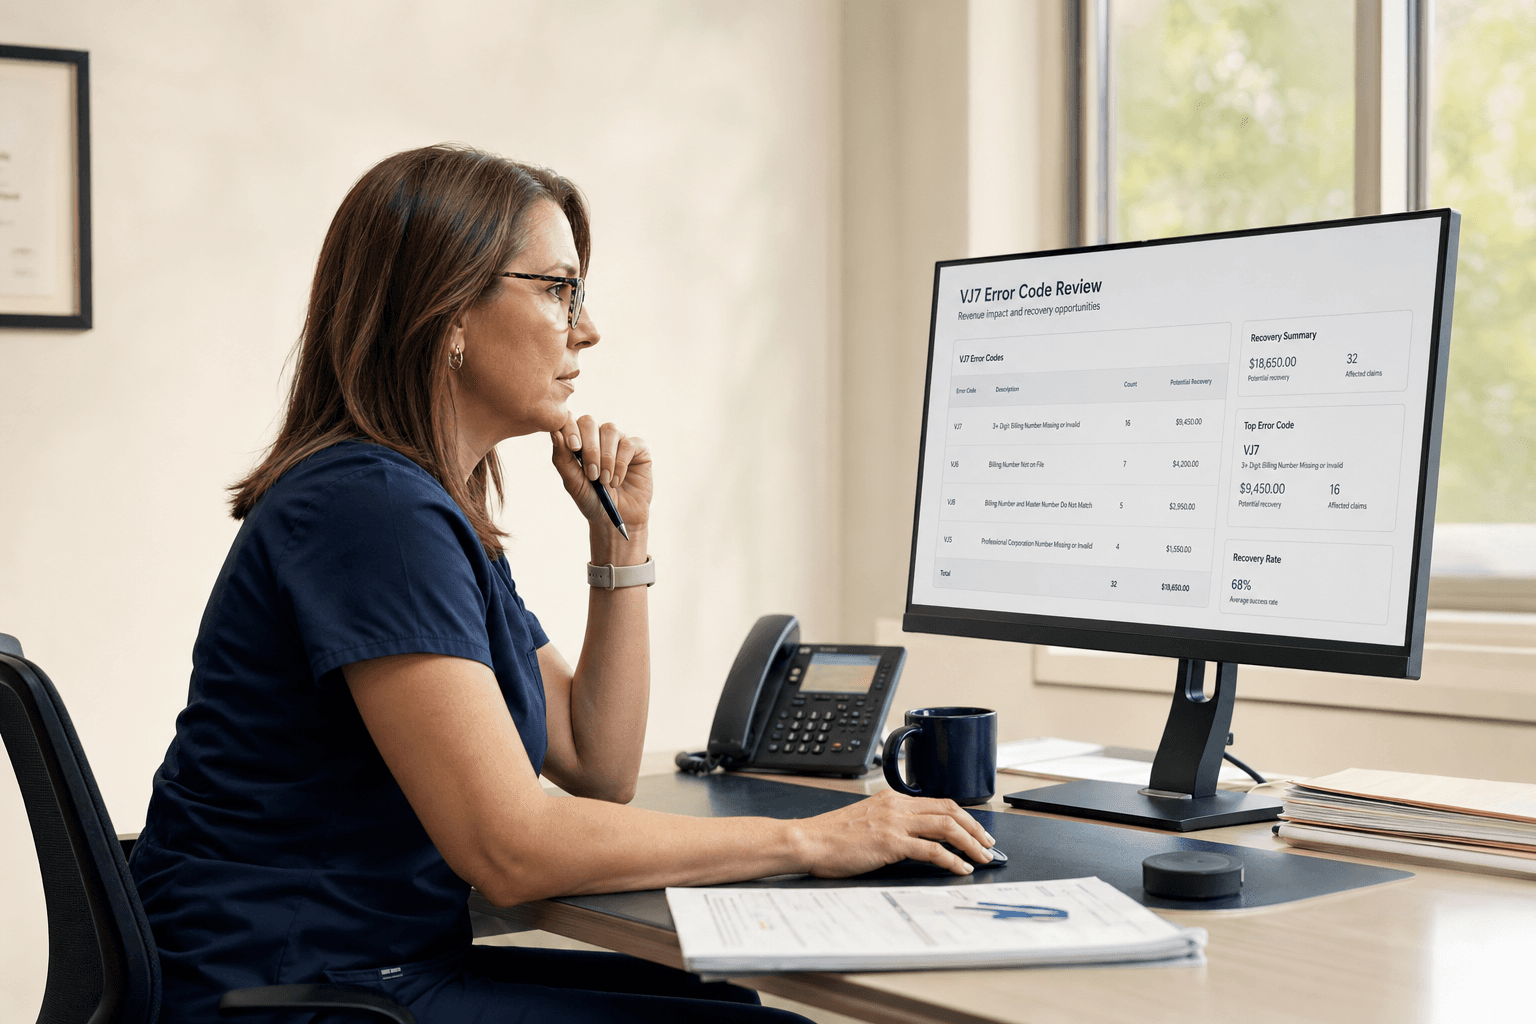
You opened your remittance advice, spotted a VJ7 rejection, and now you are wondering whether that claim is gone for good. It is not, but the window to recover it is narrower than you think, and the clock has been running since the day you rendered the service.
VJ7 is OHIP's "Stale-Dated Claim" code.1 It means the claim arrived at the Ministry after the permitted submission window had already closed. The service itself was valid. The timing was not. What you do in the next few days determines whether that revenue is recoverable or permanently written off.
Below, we walk through exactly what VJ7 means, where the clock runs out, what the right resubmission path looks like, and why a single VJ7 rejection is almost always a signal worth investigating further.
What Is Error Code VJ7, and Why Did OHIP Create It?
The VJ7 code is issued when a fee-for-service claim is submitted more than three months after the date the service was rendered. The Ministry's system flags it automatically on the Claims Error Report, no human review, no discretion, no exceptions at the electronic gateway.1
OHIP sets this boundary intentionally. Stale dating rules exist because payment disputes become harder to adjudicate as time passes, clinical memory fades, eligibility status changes, and audit trails weaken. The three-month window is a regulatory floor, not a software glitch.
What changed recently: as of April 1, 2023, the Ministry cut the historic six-month submission window down to three months. That is a significant tightening. Practices still operating on the older mental model of "six months to submit" are running directly into VJ7 rejections as a result.
The Most Dangerous Mistake Practitioners Make in the First 24 Hours
Q: When a practitioner first spots a VJ7, what is the single most common mistake they make?
The most common mistake is attempting to instantly correct and electronically resubmit the claim through their EMR or billing software, treating VJ7 like a simple data-entry error such as an invalid version code.
Because a VJ7 code indicates a stale-dated claim, the system is hardcoded to reject subsequent automated electronic transmissions immediately. Resubmitting through the standard send button does not bypass the problem. It creates a new layer of technical errors, buries the original claim deeper in the billing backlog, and increases administrative friction without recovering a single dollar.
This "double-rejection loop" compounds the damage in three specific ways:
-
Permanent revenue forfeiture risk. OHIP permanently refuses payment on over-age claims past the 90-day mark unless an official appeal path is explicitly followed. Treating VJ7 like a typo burns time while the true recovery window narrows.
-
The manual review logjam. If a practitioner bypasses proper manual override channels, the claim risks getting caught in the Ministry's manual review queue, which handles over 1.16 million flagged claims annually, with some taking months or years to resolve. That freezes cash flow on those services indefinitely.
-
Wasted administrative effort. Staff spend hours "fixing" data elements that are not the actual problem. The submission date is the problem, and only the stale-dated claims pathway addresses that.
The correct first step is to stop treating VJ7 as a data error and start treating it as a structural deadline failure requiring a specific recovery protocol.
The VJ7 Timeline: Where the Clock Runs Out Most Often
Q: Exactly when does an OHIP claim age out and trigger a VJ7 rejection?
The absolute cutoff is three months, approximately 90 days, from the date of service.1 That window is not negotiable at the electronic submission level.
In a typical clinic's submission workflow, the clock most often expires at three specific operational choke points:
1. Error Report Purgatory
Clinics generally track billing via the monthly Remittance Advice (RA) issued around the 15th of each month. But initial rejections, invalid health card version codes, EH2 errors, missing tracking details, appear much earlier on bi-weekly Claims Error Reports. Front-desk staff often leave these minor errors for month-end reconciliation.
Here is how a recoverable error becomes an unrecoverable VJ7: a service performed on January 10th is rejected on a January 25th Error Report. The team plans to fix it "later." That claim hits its stale-date wall on April 10th. If it is not corrected and successfully retransmitted before that date, a fixable front-end error becomes a permanent write-off.
2. The Mid-Month Submission Blindspot
OHIP operates on a strict monthly cycle with a processing cut-off on the 18th of each month. A clinic batching claims on the 20th assumes they are staying current with their workflow. Those claims sit idle until the next processing cycle. If a claim is already at day 80 when it misses the 18th cut-off, it will cross the 90-day threshold before the Ministry's system ever processes it, and arrive dead on arrival with a VJ7.
3. Patient Eligibility Lag
When a patient presents an invalid or expired health card, the claim is kicked back under EH2 or VH1. The billing file goes on hold while the team waits for the patient to update their version code. The 3-month OHIP clock does not pause for patient response times. If a busy clinic takes four to six weeks to chase down updated information, the remaining resubmission window disappears rapidly. The claim silently expires in the EMR backlog.
To protect against all three, shift to a weekly submission protocol and audit your EMR's "Unsubmitted" and "Error" queues every 14 days.
Is Your VJ7 a One-Off or a Sign of Something Bigger?
Q: If one VJ7 shows up, how likely is it that more are hiding in the backlog?
There is an 80% to 90% probability that a single VJ7 rejection is a signal of systemic claim aging or a process breakdown rather than an isolated typo.
Because modern billing platforms process and batch claims rapidly, a claim should not physically sit in a queue for 90-plus days unless it was neglected in a backlog, trapped in a loop of uncorrected front-end rejections, or literally forgotten. If a VJ7 has leaked through to a final remittance advice, the practice is likely suffering from unmonitored revenue leakage, the kind that does not surface in month-end reports because billing staff focus on what got paid, not what quietly aged out.
Here is a 10-minute triage you can run directly in your billing system right now:
Step 1, Eliminate the typo (the 10% scenario)
Open the specific rejected claim and cross-reference the service date with the patient's clinical chart. If the service was performed November 10th but data entry recorded October 10th, pushing it past the 3-month window artificially, that is an isolated data-entry error. Correct the date and resubmit.
If the chart date matches the claim date, the claim was genuinely held for over 90 days before submission. Proceed to step 2.
Step 2, Run an "Unsubmitted and Draft Claims" query
Generate a report of all unsubmitted, draft, or held claims sorted by date of service, oldest to newest. If you see a tail of unbilled encounters approaching or exceeding 60 to 75 days, your clinic has an unbilled backlog bottleneck.
Step 3, Run a "Rejected and Unreconciled Claims" query
Pull all outstanding rejections, errors that have not been corrected and re-batched. Look at the age of errors like EH2 (invalid version code) or VH1 (invalid health card). A claim that throws an EH2 code at day 10 but gets ignored for 80 days turns into a permanent VJ7 write-off. A backlog of old uncorrected errors is direct evidence of a failure in weekly reconciliation loops.
| Query Result | What It Diagnoses | Immediate Action | |---|---|---| | Chart date matches typo | Isolated human error | Correct the date and resubmit | | High volume of 60+ day old drafts | Provider lag or front-desk batching bottleneck | Implement a strict 48-hour card-swipe-to-billing rule | | Uncorrected errors older than 30 days | Billing staff not working monthly Error Reports | Establish weekly reconciliation protocol for all Error statuses |
This pattern is consistent with what we see in billing audits across Ontario practices. Practitioners we work with often do not spot these rejections in time because remittance advice scanning is a manual process, and billing staff rarely surface rejections by specific code to practice owners. Understanding what your billing data actually shows is a big part of why we built the approach we have. If you are not sure how to pull rejections by code in the first place, how to read OHIP remittance advice rejection codes walks through the report line by line.
How to Resubmit a Stale-Dated Claim Correctly
Q: Once a claim has a VJ7, what exactly needs to change in the resubmission process?
The claim must be removed from standard automated billing batches entirely and submitted through the Ministry of Health's dedicated stale-dated claims process. Here is what that looks like in practice:
What changes on the resubmitted claim
- Isolated file separation. The claim must not be included in a standard automated MCEDT batch. Any standard batch containing a stale claim risks full batch processing issues or immediate re-rejection.
- Dedicated file type flag. The corrected claim must be exported as an independent stale-dated file. In most EMRs, set the claim header flag to "Stale Dated Claim = YES" or generate a standalone stale claim batch.
- Manual upload selection. In the OPS BPS Secure portal or corresponding MCEDT file upload interface, manually change the upload category dropdown from the general claim file type to "Stale-dated claim file."
- Error remediation first. If the claim was delayed due to data mismatches, patient version code EH2, wrong diagnostic code, invalid billing numbers, all underlying data fields must be corrected before generating the file.2
Documentation and notification requirements
Submitting the file requires an immediate email notification package sent to ClaimsManagement@ontario.ca. Include:
- Full physician name, practice address, phone number, and 6-digit OHIP billing number (and 4-digit group number if applicable). Requests must be submitted separately per physician.
- The exact MCEDT stale-dated file number, upload date, and batch reference timestamp.
- An itemized schedule listing each claim in the batch: patient Ontario Health Number, date of service, fee schedule code(s), and billed dollar amount.
- Proof of initial timely submission (Track A): If the claim was previously submitted within the original 3-month window and rejected, attach the original Claims Error Report showing the initial run date fell within 3 months of service.
- Extenuating circumstances letter (Track B): If the claim was never submitted within the initial 3-month window, attach a formal letter on clinical letterhead signed personally by the physician, not a billing agent or administrative staff, outlining the extenuating circumstances. Accepted examples include retroactively reinstated OHIP eligibility, severe system outages, or documented administrative incapacitation.
The rejection thresholds you need to know
- Day 90: Standard automated electronic acceptance ends. Any automated resubmission past this point bounces immediately with another VJ7.
- Approaching 6 to 12 months: Claims branch managers routinely deny stale authorization unless extreme medical or legal conditions apply.
- Past the RAI window (4 months from formal remittance notification): If a claim reaches a final written refusal, the balance becomes permanently unrecoverable through OHIP and must be formally appealed to the Health Services Appeal and Review Board (HSARB) within 30 days of the refusal notice.
The good news: practitioners who follow this protocol correctly can recover claims that look lost. Most just do not know the window exists or the steps required to use it.
Why Billing Software Alone Will Not Protect You
Q: Can billing software catch and flag VJ7 claims before they expire?
Automation confidence breaks down because billing software relies on static rules, while claim submission windows are moving targets tied to regulatory timelines and claim-specific history. Software helps, but relying solely on automated alerts creates a false sense of security that regularly leads to unexpected write-offs.
Where the software assumption fails
- The clean claim blindspot. Most software flags claims based on service date. If a claim is rejected for a minor data error, it sits in an error log. The software may no longer track it as an active, aging claim, letting it quietly blow past the stale-dated deadline.
- Custom payer windows. Software defaults to standard provincial timelines. It rarely accounts for specialized third-party payers, worker's compensation boards, or out-of-province insurers that enforce stricter 30-, 60-, or 90-day submission windows.
- Batching delays. If the software's alert trigger is tied to the submission date rather than the service date, it will not warn you that a draft already in the system is aging toward expiry.
The non-negotiable manual step
The absolute non-negotiable is a weekly reconciliation of the "Unsubmitted and Rejected Claims Log" matched against a strict service-date countdown. Supervisors cannot simply look at total accounts receivable balances. They must manually audit the oldest items in the queue every week, sorted by original date of service, not the date the error occurred or the date the claim was batched.
If a claim is within 45 days of its stale-dated deadline and still lacks a "Paid" or "Accepted" status, it must be manually pushed through or appealed immediately. Automation is a safety net. Manual reconciliation is the anchor.
This is also why the choice of billing infrastructure matters more than most physician-owners realize, the guide to medical billing systems for Ontario physicians covers how to evaluate whether your current setup gives you the visibility you actually need. For the wider reconciliation routine that keeps claims out of VJ7 territory in the first place, our framework for navigating OHIP rejections sets out the weekly cadence.
If this is useful in your practice, you can start with a look at what is still recoverable.
Stay connected

Frequently Asked Questions
Q: Can I still get paid after receiving a VJ7 rejection?
Yes, but only through the Ministry's dedicated stale-dated claims pathway, not through a standard electronic resubmission. You need to prepare a separate stale-dated file, upload it through MCEDT with the correct file type designation, and send a notification package to ClaimsManagement@ontario.ca with proof of prior timely submission or a signed physician letter outlining extenuating circumstances. The window narrows the longer you wait.
Q: Does a VJ7 mean the service itself was denied?
No. A VJ7 rejection is a timing rejection, not a service denial. OHIP is not saying the service was inappropriate or unbillable. It is saying the claim arrived too late under current submission rules. The clinical encounter was valid, the submission deadline was missed.
Q: What is the exact cutoff that triggers a VJ7?
Three months from the date of service, approximately 90 days. This window was tightened from six months to three months on April 1, 2023.1 Any fee-for-service claim submitted after that threshold triggers an automatic VJ7 on the Claims Error Report.
Q: What is the difference between VJ7 and other timing-related rejection codes?
VJ7 specifically indicates a stale-dated claim, the submission window has fully closed. Other codes like EH2 (invalid health card version) or VH1 (invalid health card) are front-end eligibility errors that, if left uncorrected, can eventually age into VJ7 territory. VJ7 is often the end state of an EH2 or VH1 error that sat unresolved past the 90-day mark.1 The same ageing pattern applies to AT3 rejections, which are correctable on the day they appear and unrecoverable once the submission window closes.
Q: Does my billing software automatically flag claims approaching the stale-dated deadline?
Some platforms provide aging alerts, but none reliably catch every scenario, particularly claims stuck in error status that the system no longer tracks as actively aging. The only dependable safeguard is a weekly manual audit of your unsubmitted and rejected claims queue, sorted by original date of service. If a claim is within 45 days of its stale-date limit and not yet accepted, treat it as urgent.
If you found a VJ7 on your remittance advice this month, there is a reasonable chance more are sitting in your claims backlog right now, quietly aging past the recovery threshold. We look at this specifically: which claims are approaching the deadline, which have already crossed it, and what the recovery path looks like. See what is sitting in your rejected claims. You pay a percentage of what comes back, and nothing if nothing is recovered. Practices that want the reconciliation handled every cycle afterwards move to Claims Concierge.
References
- Ontario Ministry of Health, Remittance Advice Explanatory Codes/Messages (April 2026). ontario.ca.
- Ontario Ministry of Health, OHIP INFOBulletins 2026: Bulletin 260506 PSA-Related Fee Schedule Code Adjustments. ontario.ca.
- Ontario Ministry of Health, Diagnostic Codes and Claims Submission Resources (March 2026). ontario.ca.
Prefer a broader look at your billing setup? See how ongoing billing works.